Breast Augmentation Malaysia: Implants or Fat Transfer
Questions patients ask before choosing a volume method
When someone in Malaysia or elsewhere starts researching breast enlargement, the first fork is usually the same: implants, or transfer of the patient’s own fat. Both paths sit under the wider label of breast augmentation, and both are elective surgery with real recovery, real risk, and no guaranteed aesthetic outcome. This piece gathers questions patients commonly ask when comparing options and explains why implant follow-up still matters years later. It is not medical advice and does not recommend any clinic or surgeon.
What implant-based augmentation can and cannot do
The American Society of Plastic Surgeons overview of breast augmentation describes implant surgery as a way to increase fullness, improve balance with the hips, or address volume loss after pregnancy or weight change. It also states clearly what surgery cannot fix on its own: marked ptosis (droop) usually needs a lift, with or without implants. International patient material from ISAPS on breast augmentation likewise frames implants as devices placed in a planned pocket (subglandular, submuscular, or related planes), with capsular contracture listed among the more frequent device-related issues that follow-up visits help detect.
Patients often ask about cup size. Surgeons typically plan by volume in cubic centimetres and chest measurements, not retailer cup letters, because bra sizing varies. Another frequent question is lifespan. Implants are not lifetime devices; future revision can be needed for rupture, contracture, position change, or a personal wish to alter size. That reality is why monitoring belongs in the same conversation as the operation itself.

When autologous fat transfer is the quieter option
transferring your own fat to the breast (autologous fat grafting) harvests fat by liposuction, processes it, and injects it into the breast. Societies group it with augmentation methods that use the patient’s own tissue rather than a manufactured implant. Typical patient questions cluster around three limits: you need enough donor fat; retained volume is usually modest compared with implants; and a share of transferred fat may be reabsorbed, so more than one session is sometimes discussed.
Fat grafting can also refine contour after prior surgery or soft tissue thinning over an implant, which is a different clinical goal from “go up several cup sizes in one sitting.” Hybrid plans that combine a smaller implant with fat exist in some practices; those still leave the implant on a long-term monitoring pathway. A short educational comparison of the two volume methods is useful background before a consultation, not a substitute for examination.
Brief clinician explainer on fat transfer versus implants: donor-fat limits, modest volume change, and the more immediate volume of devices. Educational only; local clinical advice takes priority.
Why follow-up implant checks still matter
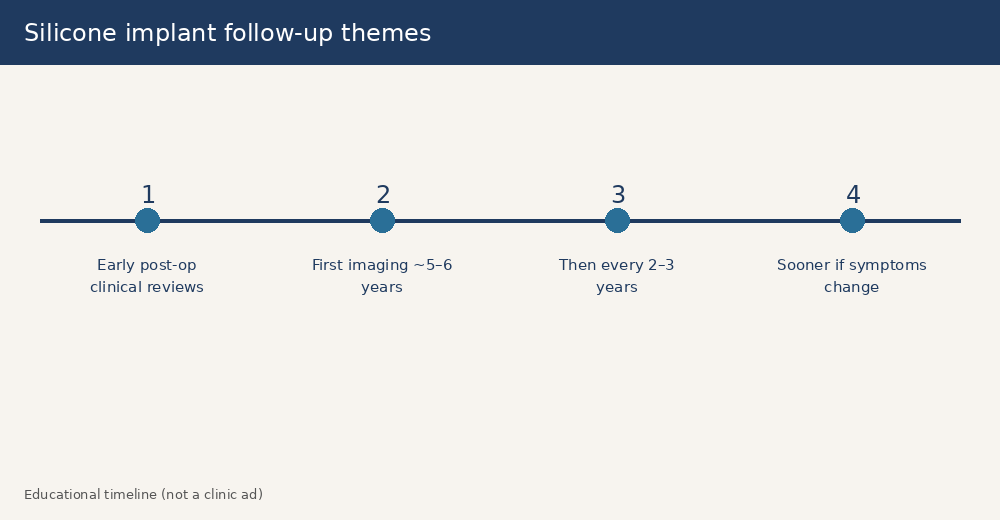
Anyone who already has silicone implants, or who chooses them now, should understand surveillance separately from cancer screening. The U.S. FDA consumer update on breast implants stresses that implants are not lifetime devices and that silicone implants warrant imaging to look for silent rupture. Common labelling guidance cited by plastic-surgery societies points to a first ultrasound or MRI around five to six years after placement, then every two to three years, with MRI preferred if symptoms appear or ultrasound findings are unclear. ASPS safety pages align with that screening theme and add that routine clinical review remains part of breast and device health.
A structured breast implant check-up typically covers history, examination, and often ultrasound as a first-line look at integrity and position. Patients ask whether “no symptoms” means “no need to check.” Silent rupture is exactly why asymptomatic imaging appears in regulatory guidance. New pain, hardness, swelling, shape change, or systemic concerns should prompt earlier clinical review, not a wait for the calendar year.
Consultation notes worth writing in your own words
Write answers in your own words before you decide. How much volume change do you actually want, and is that realistic with fat alone? If implants are discussed, which fill, shape, and pocket plane are proposed, and what revision rate does that surgeon see? What is the plan for mammograms plus implant imaging later? If you already have devices placed years ago, when was the last clinical and ultrasound or MRI review?
Then ask one planning question for this month: if you needed another procedure in ten years for rupture, contracture, or change of preference, would today’s choice still feel honest for your anatomy and lifestyle?